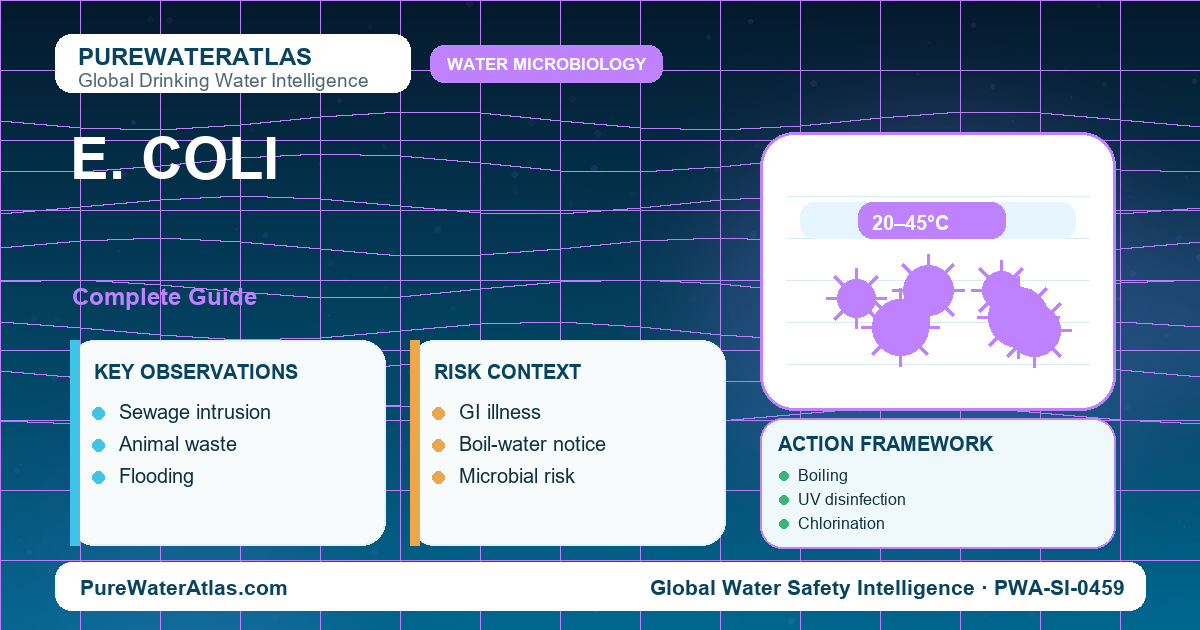
Escherichia coli (E. coli) is one of the most important indicators used to assess fecal contamination of drinking water. When E. coli is found in a water sample, it indicates that fecal material from humans or animals has entered the water supply or system and that enteric pathogens may also be present. It does not, by itself, prove that a particular disease-causing organism or pathogenic E. coli strain is present.
That distinction matters. Many E. coli strains normally live in the intestines of humans and warm-blooded animals without causing illness, while some strains can cause serious disease. In drinking-water monitoring, however, E. coli is important primarily because it is a relatively specific marker of fecal contamination. A positive result therefore calls for both immediate exposure precautions and investigation of how the contamination occurred.
What E. coli in drinking water means
Indicator detection vs a specific pathogen
E. coli is a bacterium commonly found in the digestive tracts of humans and other warm-blooded animals. In water-quality work, its principal role is as an indicator of fecal contamination. Health Canada notes that detecting E. coli indicates fecal contamination and an increased possibility that enteric pathogens are present, but does not identify which pathogens, if any, are in the sample.
Not all E. coli strains are equally harmful. Some pathogenic strains can cause gastrointestinal disease, but an ordinary drinking-water E. coli indicator test should not be interpreted as proof that a specific pathogenic strain is present. Conversely, finding an apparently non-pathogenic indicator organism does not make the contamination unimportant: fecal material can carry viruses, protozoa and other bacteria that were not measured by the test.
E. coli cannot be reliably detected by appearance, taste or smell. Clear, odorless water may still be microbiologically contaminated. A widely used drinking-water target is no detectable E. coli in 100 mL; specific legal standards and response procedures nevertheless depend on the jurisdiction and type of water system.
What a negative result can—and cannot—tell you
An E. coli-not-detected result means the organism was not found in that particular sample using the test performed. It is reassuring, but it is not a guarantee that the supply is always free of fecal contamination or every waterborne pathogen. Contamination can be intermittent, particularly after rainfall, flooding, pressure changes or failures of a sanitary barrier.
This is why a single clean test does not override evidence of a damaged well, sewage intrusion or another known vulnerability. Water safety depends on sampling alongside source protection, infrastructure condition and treatment performance. For broader context on microbial hazards, see the guides to bacteria in drinking water and waterborne pathogens in drinking water.
Why E. coli is used as a fecal-contamination indicator
Why indicator organisms are practical
Directly testing water for every possible pathogen would be technically difficult and impractical for routine monitoring. Water programs therefore use indicator organisms that can reveal failures in the barriers intended to keep fecal material out of drinking water.
E. coli is especially useful because it occurs in human and animal feces in high numbers, is predominantly fecal in origin, generally does not multiply in drinking water, and can be detected with established, relatively rapid methods. These properties have made it one of the world’s most widely used indicators of fecal contamination, according to Health Canada’s technical review.
An indicator is not a pathogen inventory. The concentration or absence of E. coli cannot reliably tell a laboratory whether a particular virus, protozoan or pathogenic bacterial strain is present. Its value is that it signals whether a fundamental sanitary barrier may have failed. This indicator-based approach fits the broader multiple-barrier, risk-management framework reflected in the World Health Organization’s Guidelines for Drinking-water Quality.
How E. coli reaches wells and water systems
Sewage, septic systems, runoff and animals
The principal routes involve movement of fecal material into source water. Sewage releases, leaking sanitary sewers, wastewater discharges, failing septic systems, agricultural runoff and fecal material from animals can all contribute contamination. Heavy rainfall and flooding can mobilize material that would otherwise remain separated from a water source.
Private septic systems are particularly relevant to wells. If a system is failing, improperly sited or poorly maintained, contaminated water can migrate toward groundwater. Vulnerability depends on local hydrogeology as well as construction: shallow groundwater, permeable formations and fractured rock can create rapid pathways under some conditions.
Agricultural sources include manure storage and application areas, livestock operations and runoff from land where fecal material is present. Wildlife and domestic animals can also contribute. The presence of E. coli establishes evidence of fecal contamination, however, not which human or animal source produced it.
Well construction and surface intrusion
A well can become contaminated when its physical barriers fail. Potential problems include an insecure or damaged cap, defective casing or seals, inadequate drainage around the wellhead, flooding, and work that opens the well or plumbing to contamination. Nearby septic or manure sources can add to the risk.
Testing is particularly important after flooding and well repairs because these events can create new microbial pathways even when earlier samples were satisfactory. Additional source-pathway detail is available in the guide to E. coli contamination causes and sources.
Distribution, storage and pressure events
Water can also become contaminated after treatment. Authoritative drinking-water guidance identifies pathways including contaminated storage, cross-connections, intrusion associated with pressure events, and contamination introduced during repairs. In a treated distribution system, an E. coli detection can therefore point either to inadequate treatment or to contamination entering after treatment.
Health risks and vulnerable groups
Indicator risk versus pathogenic E. coli
The central health concern from an E. coli-positive drinking-water result is possible exposure to fecal contamination. Fecal material can contain disease-causing bacteria, viruses and protozoa, so the risk is broader than the E. coli measured in the sample.
Some E. coli strains themselves are pathogenic, but routine indicator testing does not establish that one of those strains is present. It is therefore useful to keep two questions separate: whether the water shows evidence of fecal contamination, and whether a particular disease-causing organism has been identified. The first is enough to justify prompt action in drinking-water settings even when the second is unknown.
Who may need extra caution
Contaminated water can cause illness in otherwise healthy people, while susceptibility and severity vary with the organism and the person exposed. Public-health guidance gives particular attention to households that include infants or children, older adults, pregnant people, or people with weakened immune systems. These categories do not imply identical susceptibility to every E. coli strain or every waterborne disease; they indicate circumstances in which avoiding potentially contaminated water warrants particular care.
Exposure is not limited to drinking a glass of water. Water used for cooking, brushing teeth, making beverages or ice, and preparing infant formula may also be ingested. Detailed organism- and illness-level discussion is covered separately in the E. coli health-effects and risks guide.
Testing methods and interpreting a positive result
How E. coli is tested
E. coli cannot be ruled in or out by inspecting the water. Laboratory testing is necessary. Standard drinking-water methods include membrane-filtration and enzyme-substrate approaches, among others. Depending on the method and monitoring program, results may be expressed as presence or absence in a specified sample volume or as a quantitative bacterial count.
Method choice matters because different tests answer different questions. Routine indicator methods are not equivalent to molecular testing for a particular pathogenic strain. Regulatory acceptability also depends on the applicable drinking-water program, so samples intended for compliance or health decisions should be collected and analyzed according to the laboratory’s or authority’s instructions.
Private-well owners should generally use a certified or accredited drinking-water laboratory where required or available and follow its directions for sample collection, labeling, storage and transport. Poor sampling can undermine an otherwise accurate laboratory method. The home water testing guide covers sampling and test selection in more detail, while the E. coli testing and detection guide examines analytical methods specifically.
How to read common results
| Test result | Interpretation | Immediate action | Follow-up |
|---|---|---|---|
| E. coli detected | Evidence of fecal contamination; enteric pathogens may also be present. For a private well, authoritative guidance treats this as unsafe drinking water until the problem is addressed. | Follow local health guidance. Use boiled water or another known-safe source for uses covered by the advisory, such as drinking, cooking and tooth brushing. | Resample or confirm as directed, inspect for contamination routes and defects, make repairs, disinfect where appropriate, and retest to verify corrective work. |
| Total coliform detected; E. coli not detected | Indicates a potential microbiological, treatment or distribution-system integrity problem, but is less specific for fecal contamination. | Follow the laboratory, utility or health authority’s instructions. U.S. regulated public systems have prescribed repeat and E. coli testing procedures. | Complete repeat testing and system assessment as applicable; investigate recurring detections. |
| E. coli not detected | No E. coli was found in that sample. This does not rule out intermittent fecal contamination or every pathogen. | Normally no action is needed solely because of this result, unless an advisory or known system vulnerability remains in effect. | Continue scheduled testing and correct known sanitary defects regardless of a single negative sample. |
Why one sample is not the whole picture
A positive E. coli result identifies a sanitary problem but usually does not identify its exact source. A negative result, meanwhile, captures conditions only at the place and time sampled. Repeated testing and inspection may therefore be necessary when contamination is intermittent or a structural problem is suspected.
This is also why testing should not be separated from investigation. Repeatedly disinfecting a contaminated well without determining whether surface water, septic leakage or a defective wellhead is responsible can suppress the immediate microbial finding while leaving the underlying route intact.
Immediate actions after detection
For a customer of a public water system, the utility and local health authority’s instructions take priority because they know the extent of the event and the required response. For a private well, a positive E. coli result calls for a safe alternative supply or appropriate boiling while investigation and corrective work proceed. Health Canada’s private-well guidance, for example, directs users to boiled water or another safe source for drinking, cooking and tooth brushing after E. coli is detected.
When boiling is appropriate
Boiling is an effective emergency measure for microbial contamination when health authorities recommend it. CDC guidance calls for bringing water to a full rolling boil for 1 minute, or 3 minutes at elevations above 6,500 feet, unless local authorities provide different instructions. Water should then be allowed to cool safely.
An active advisory should also determine how water is handled for food preparation, tooth brushing, ice and other household uses. More detail is available in the boiling water purification guide.
What boiling does not solve
Boiling controls microbial hazards; it does not remove harmful chemical contaminants or toxins. CDC specifically warns that boiling chemically contaminated water does not make it safe. A chemical incident may require a do-not-drink or do-not-use instruction instead of a boil-water advisory.
Boiling also does not repair a cracked well casing, eliminate a sewage pathway or restore a failed treatment barrier. It reduces exposure while the microbial problem is being resolved. An E. coli detection therefore requires appropriate source or system investigation, corrective action and verification testing—not just temporary treatment of water used at the tap.
Disinfection, remediation and retesting
Find and fix the contamination route
Corrective work starts with the reason contamination entered the supply. For a well, that can mean examining the wellhead, cap, casing, seals, pump and plumbing; checking drainage and evidence of flooding; considering nearby septic or manure sources; and inspecting any existing treatment equipment. Defects that permit contamination should be corrected before the problem is considered resolved.
This distinction between remediation and disinfection is fundamental. Disinfection can inactivate E. coli already in a well or plumbing system, but a continuing route of fecal entry can contaminate the system again.
Disinfection and treatment options
Chlorination can inactivate E. coli when an appropriate disinfectant concentration and contact time are achieved. Ultraviolet systems can also inactivate bacteria, provided the equipment is properly designed, operated and maintained and the incoming water quality is suitable. Treatment trains may use filtration before disinfection when particles or turbidity would interfere with the process.
Shock chlorination is commonly used for an undisinfected private well after appropriate investigation and repairs, including following some contamination events or well work. There is no useful universal bleach dose: the procedure depends on well dimensions, disinfectant concentration, plumbing configuration and local requirements. Well owners should follow instructions from the relevant health authority or qualified well professional rather than improvising a dose.
Where contamination persists, further source investigation may lead to well reconstruction or replacement, correction of septic or drainage problems, validated continuous treatment, or use of another safe water supply. The effective long-term strategy is layered: protect the source, maintain the infrastructure, monitor the water and use reliable treatment where it is needed.
Retesting after corrective work
Retesting verifies whether corrective action worked. Timing matters because residual disinfectant after shock chlorination can interfere with the purpose of a post-treatment microbiological sample. The appropriate interval should therefore follow the relevant laboratory or public-health program rather than a universal timetable.
For example, Canadian guidance includes specified waiting and repeat-sampling procedures after private-well disinfection and recommends later sampling to check for recurrence. Those intervals should not be assumed to be the rules for a U.S. well or for lifting a public-system advisory elsewhere. Persistent or recurring E. coli after corrective work is evidence that the contamination route needs further investigation.
Private wells vs public systems
Private-well owner responsibilities
Private wells generally do not operate under the same routine compliance framework as public water systems, and the legal arrangements vary by jurisdiction. Owners commonly bear responsibility for testing, maintenance and corrective action. In the United States, EPA recommends testing private wells annually for total coliform bacteria, nitrate, total dissolved solids and pH, with additional testing after events such as flooding or well repairs and when nearby conditions or the water itself change significantly.
Annual testing is not a guarantee that annual sampling is sufficient for every well. A flood, damaged wellhead, septic problem or other new vulnerability is a reason to test outside the routine schedule. Owners should use their state or local requirements and accredited or certified laboratory instructions when making health decisions.
U.S. public-system requirements
U.S. public water systems are governed by federal and state drinking-water requirements rather than owner-managed well guidance. Under EPA’s Revised Total Coliform Rule, total-coliform-positive routine or repeat samples are analyzed for E. coli, and specified results can trigger repeat monitoring, assessments and correction of sanitary defects.
An important regulatory distinction is that an E. coli detection is not synonymous with an EPA E. coli maximum contaminant level violation. The rule defines violations through specified combinations of routine and repeat results and certain monitoring failures. Consumers served by a public system should therefore follow the utility and health authority’s notice rather than trying to apply private-well remediation procedures to the public supply.
E. coli vs total coliforms and other indicators
E. coli vs total coliforms
Total coliforms and E. coli are related monitoring concepts but should not be treated as interchangeable. Total coliforms are a broader bacterial group used to reveal problems with microbiological water quality, treatment performance or distribution-system integrity. A total-coliform-positive result alone is not specific proof that fecal contamination occurred.
E. coli is more specifically associated with fecal material. Its detection consequently carries a different interpretation: fecal contamination has occurred and enteric pathogens may also be present. Older references to “fecal coliforms” should not be read as though that category were simply another name for E. coli; E. coli provides the more specific fecal indicator in modern drinking-water interpretation.
Where HPC fits
| Indicator | Indicates | Does not indicate |
|---|---|---|
| E. coli | Fecal contamination and an increased possibility that fecal pathogens are present. | Does not identify a particular pathogen or prove that every pathogen is present or absent. |
| Total coliforms | General microbiological condition and possible treatment or distribution-system integrity problems. | A positive result alone is not specific proof of fecal contamination. |
| Heterotrophic plate count (HPC) | General microbiological water quality and populations of culturable heterotrophic microorganisms under the test conditions. | It is not a specific fecal-contamination indicator and does not substitute for E. coli testing. |
These distinctions explain why no single microbial result describes every aspect of water safety. E. coli is valuable because of what it says about fecal contamination, while total coliforms and HPC provide different information about microbiological conditions and system performance.
The practical conclusion after an E. coli detection is therefore two-part. Control exposure immediately according to the applicable health guidance, using boiling or a known-safe water source when directed; then identify and correct the route by which contamination entered the water and verify the correction with appropriate testing. Boiling can address microbial exposure in an emergency, but it cannot repair the source of contamination and it cannot make chemically contaminated water safe.
Read the full guide: Water Microbiology Guide
Explore more in this category: Water Microbiology Articles